-
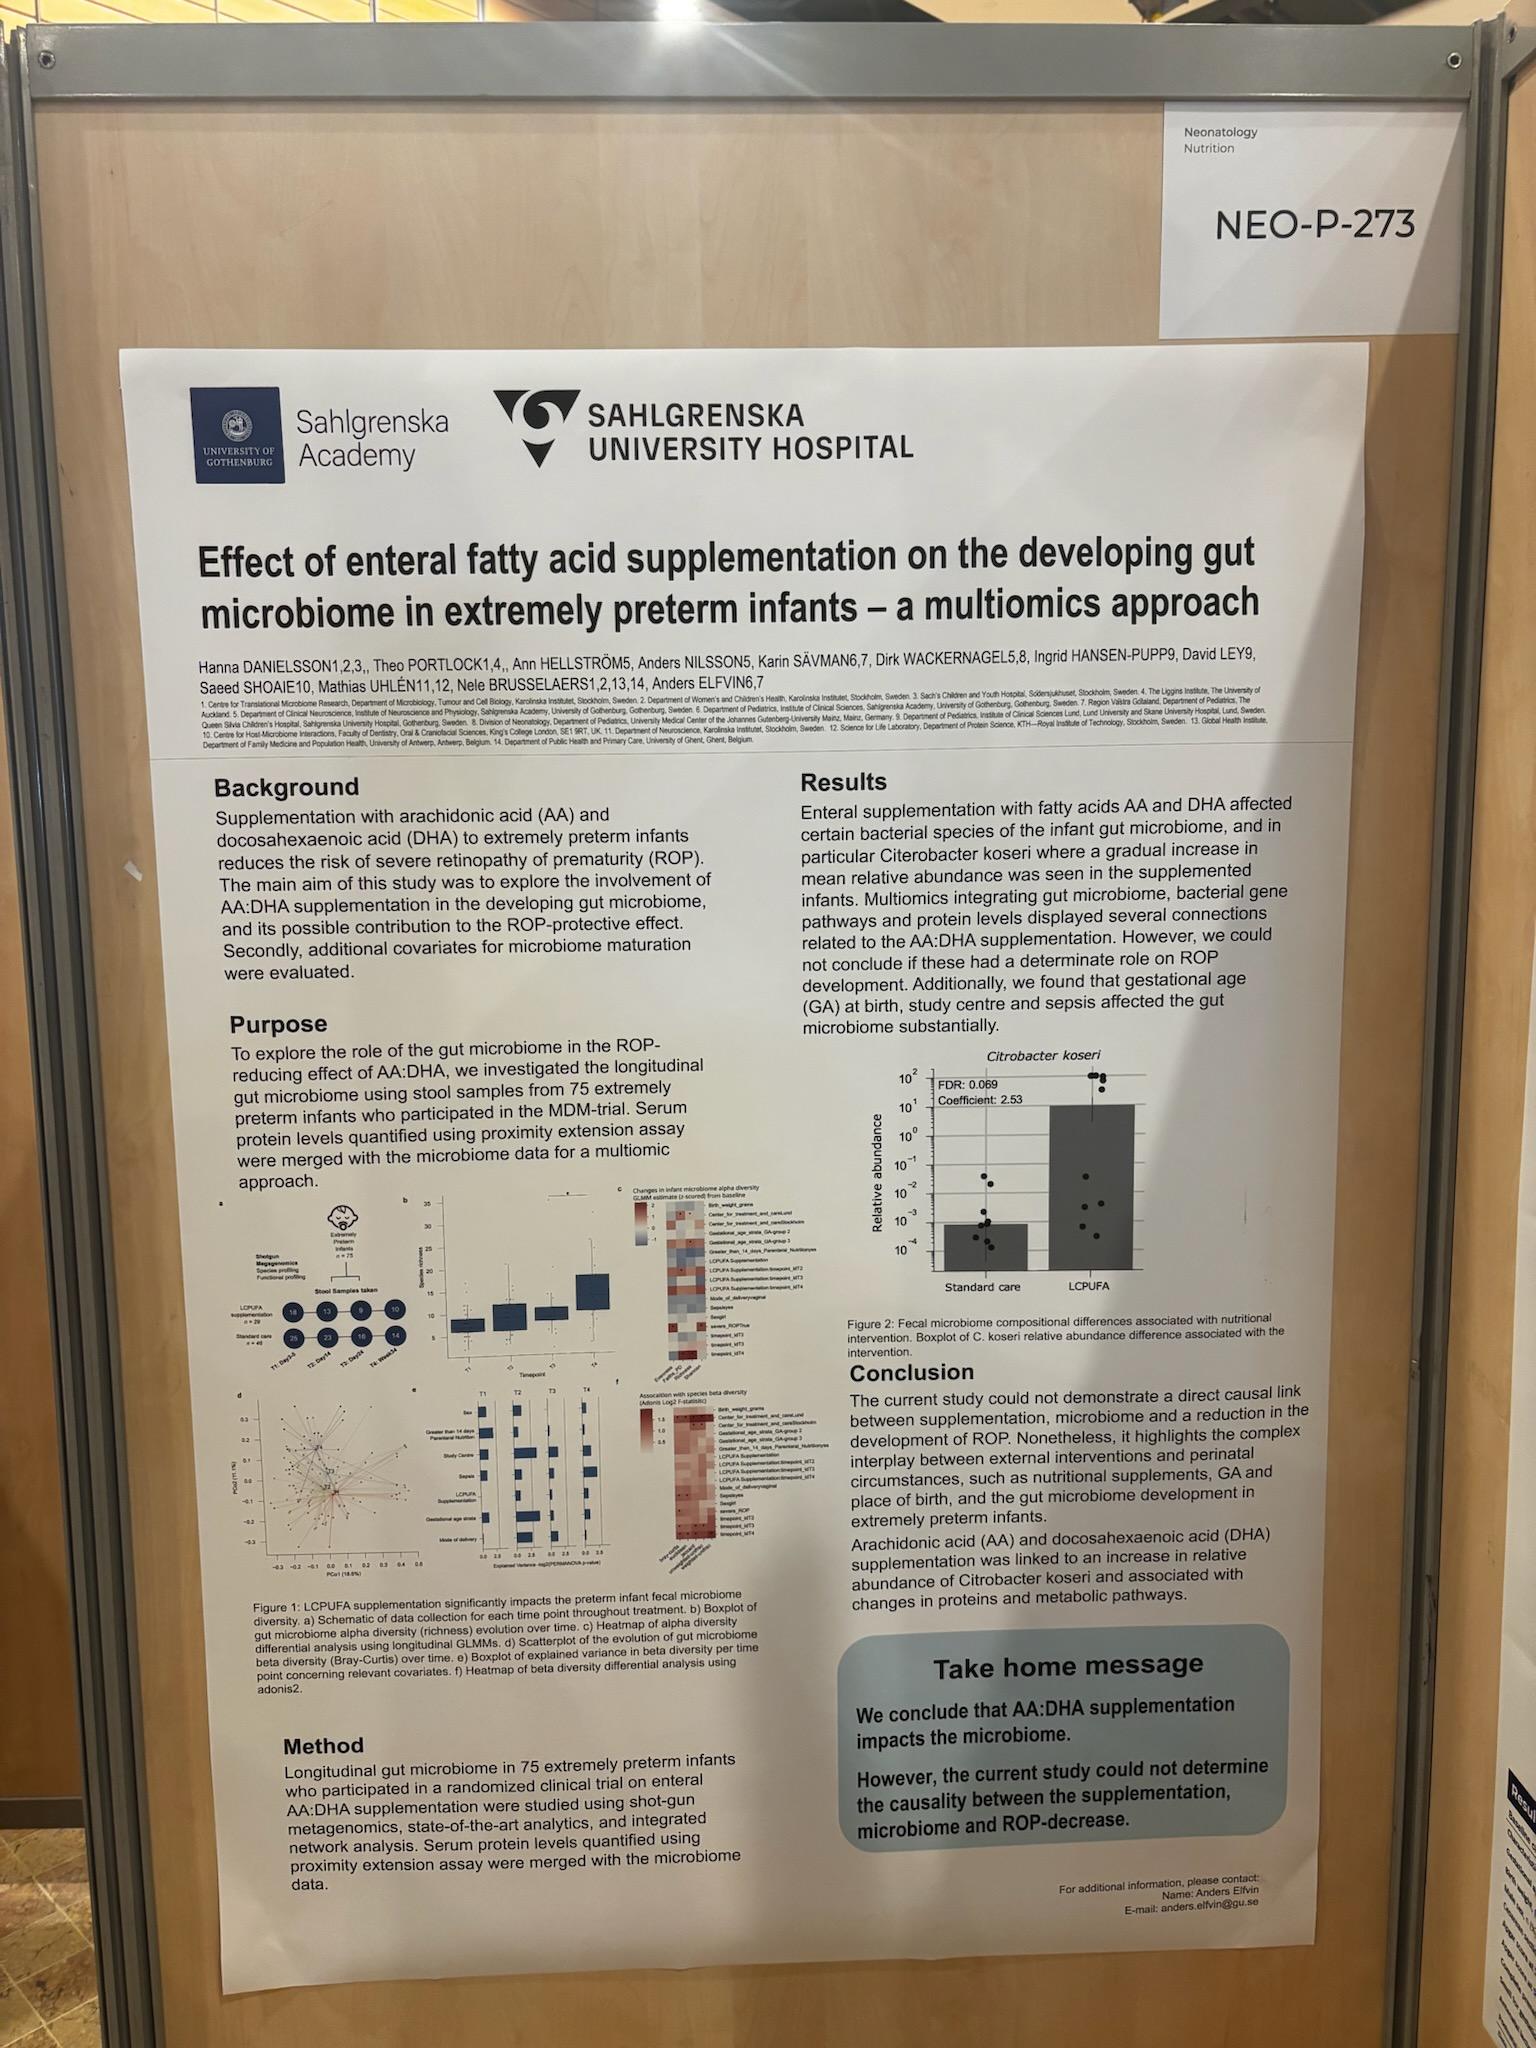
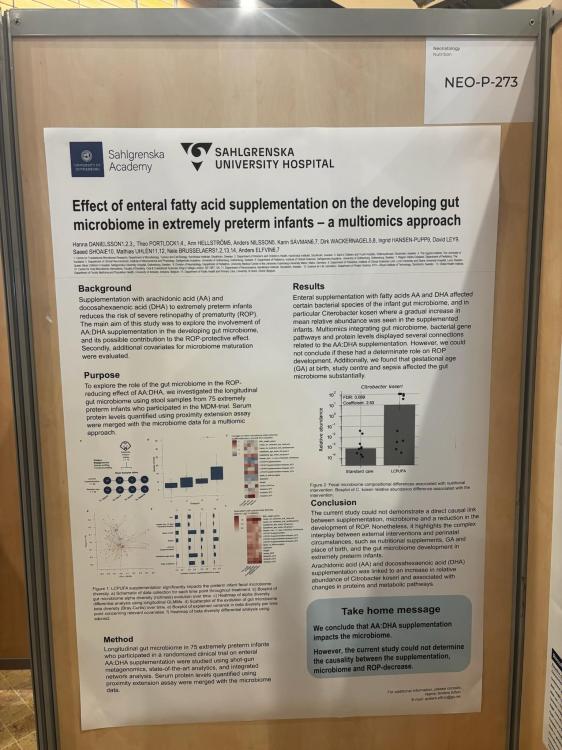
This CEPAS poster presents data on the effects of enteral arachidonic acid (ARA) and docosahexaenoic acid (DHA) supplementation on the developing gut microbiome. The researchers analysed stool samples from 75 extremely preterm infants participating in the MegaDonnaMega trial of ARA/DHA supplementation, using a multiomics approach. In short, they combined microbiome, bacterial gene pathways and protein analyses. ARA/DHA supplementation was associated with changes in gut microbiome composition. The analyses also identified changes in bacterial metabolic pathways and protein profiles. Gestational age, study centre, and sepsis were also associated with substantial effects on microbiome development. Although the original trial demonstrated a reduction in severe retinopathy of prematurity (ROP) with ARA/DHA supplementation, this study could not establish whether the microbiome changes contributed to that protective effect.
-
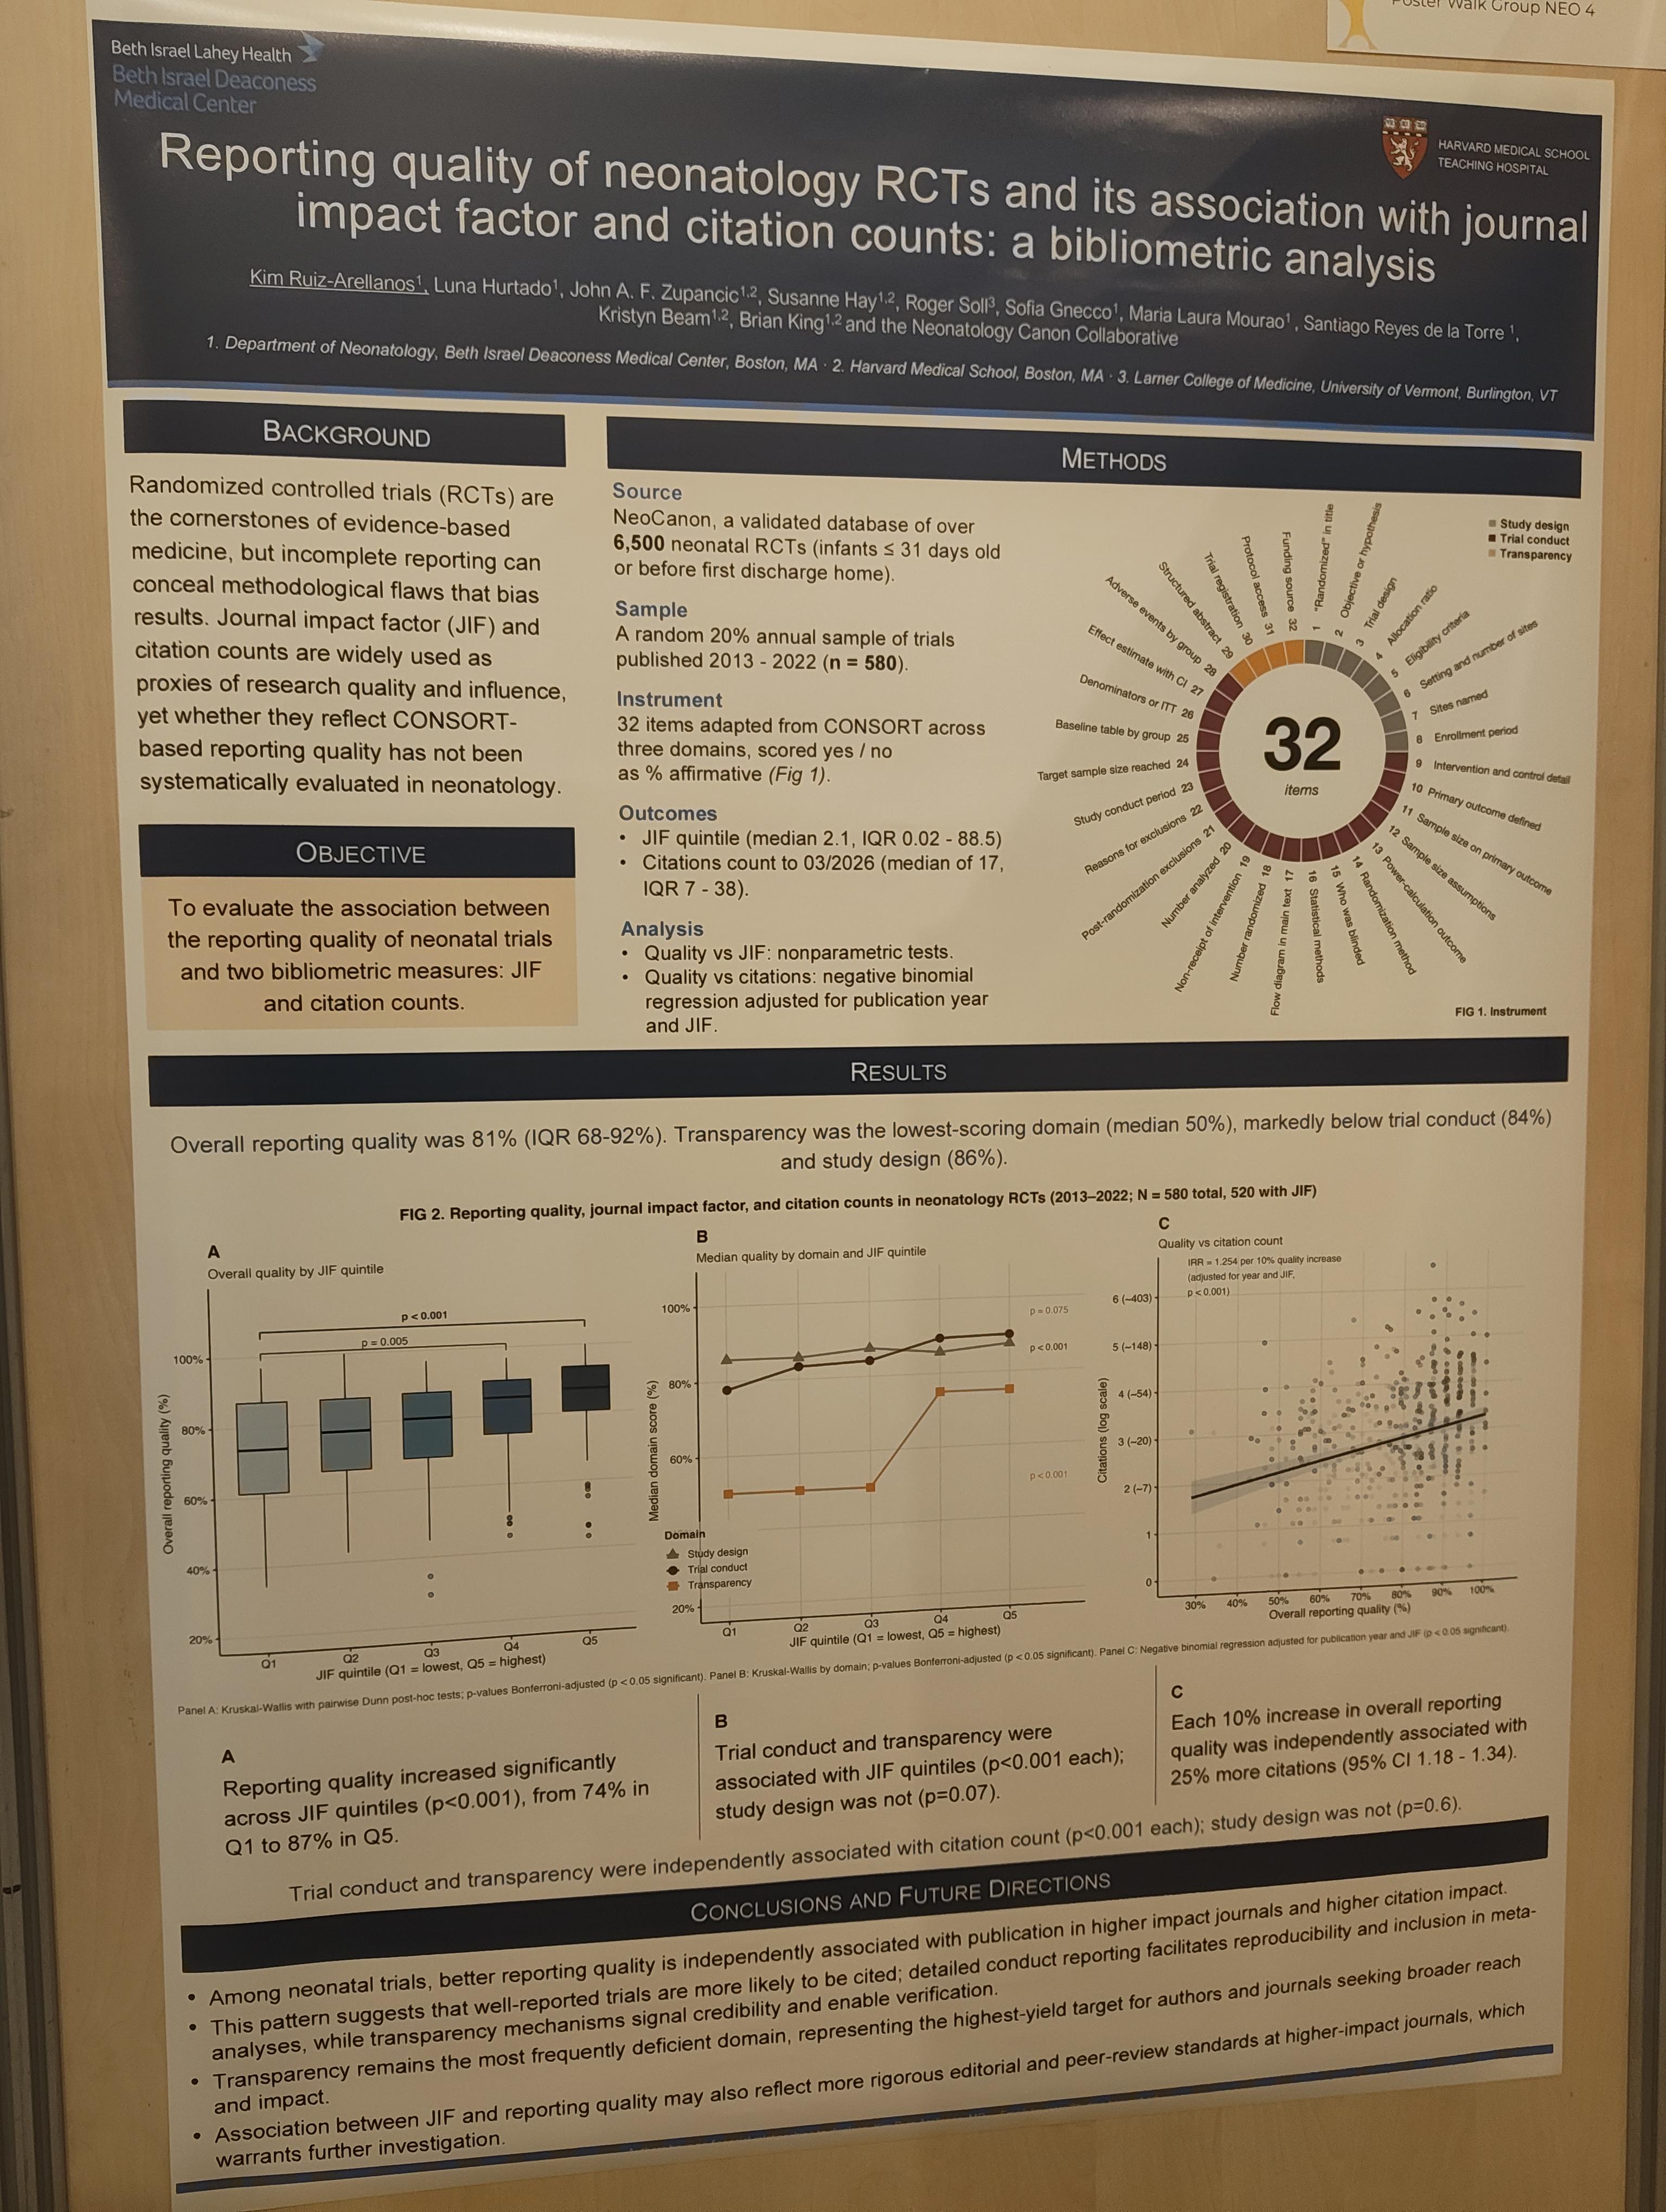
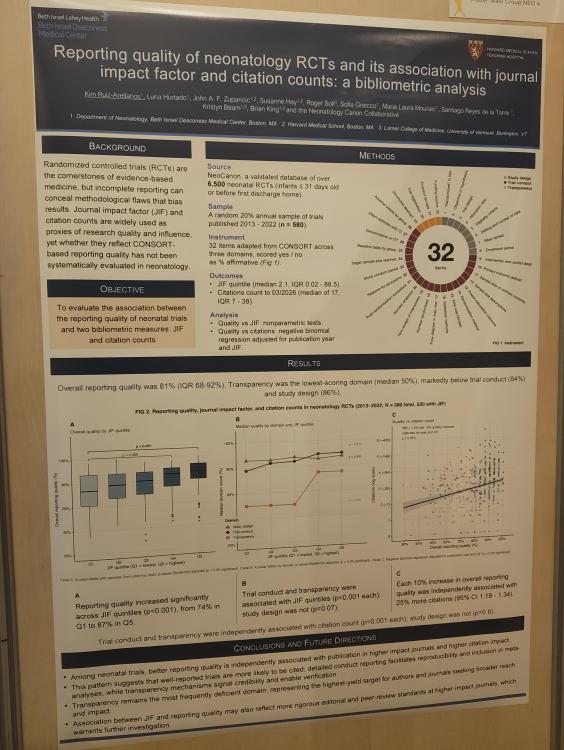
This study explored the reporting quality of randomized controlled trials (RCTs) and its association with journal impact factor and citation counts. In total, the research team evaluated 580 RCTs published between 2013 and 2022, using 32 reporting items adapted from CONSORT guidelines. Overall reporting quality was relatively good, with a median score of 81%. However, transparency was the weakest area, scoring only 50%, compared with 84% for trial conduct and 86% for study design. Reporting quality increased significantly with journal impact factor, from 74% in the lowest journal impact factor quintile to 87% in the highest. Interestingly, each 10% increase in reporting quality was associated with 25% more citations, even after adjusting for publication year and journal impact factor.
-
A 20th anniversary calls for cake! The core 99nicu Team got together last night after the CEPAS sessions, for a small celebration of these twenty years of sharing, learning and connecting. I wrote in an earlier Anniversary post that 99nicu began with a simple idea. We wanted to create a space for NICU colleagues to share and learn from one another. That spirit is still at the heart of our community. A big thank you to everyone through our 20y journey. While only the core team made it to this cake break, this anniversary belongs to all of us. So, consider this a virtual slice for the whole 99nicu community! 🙂
-
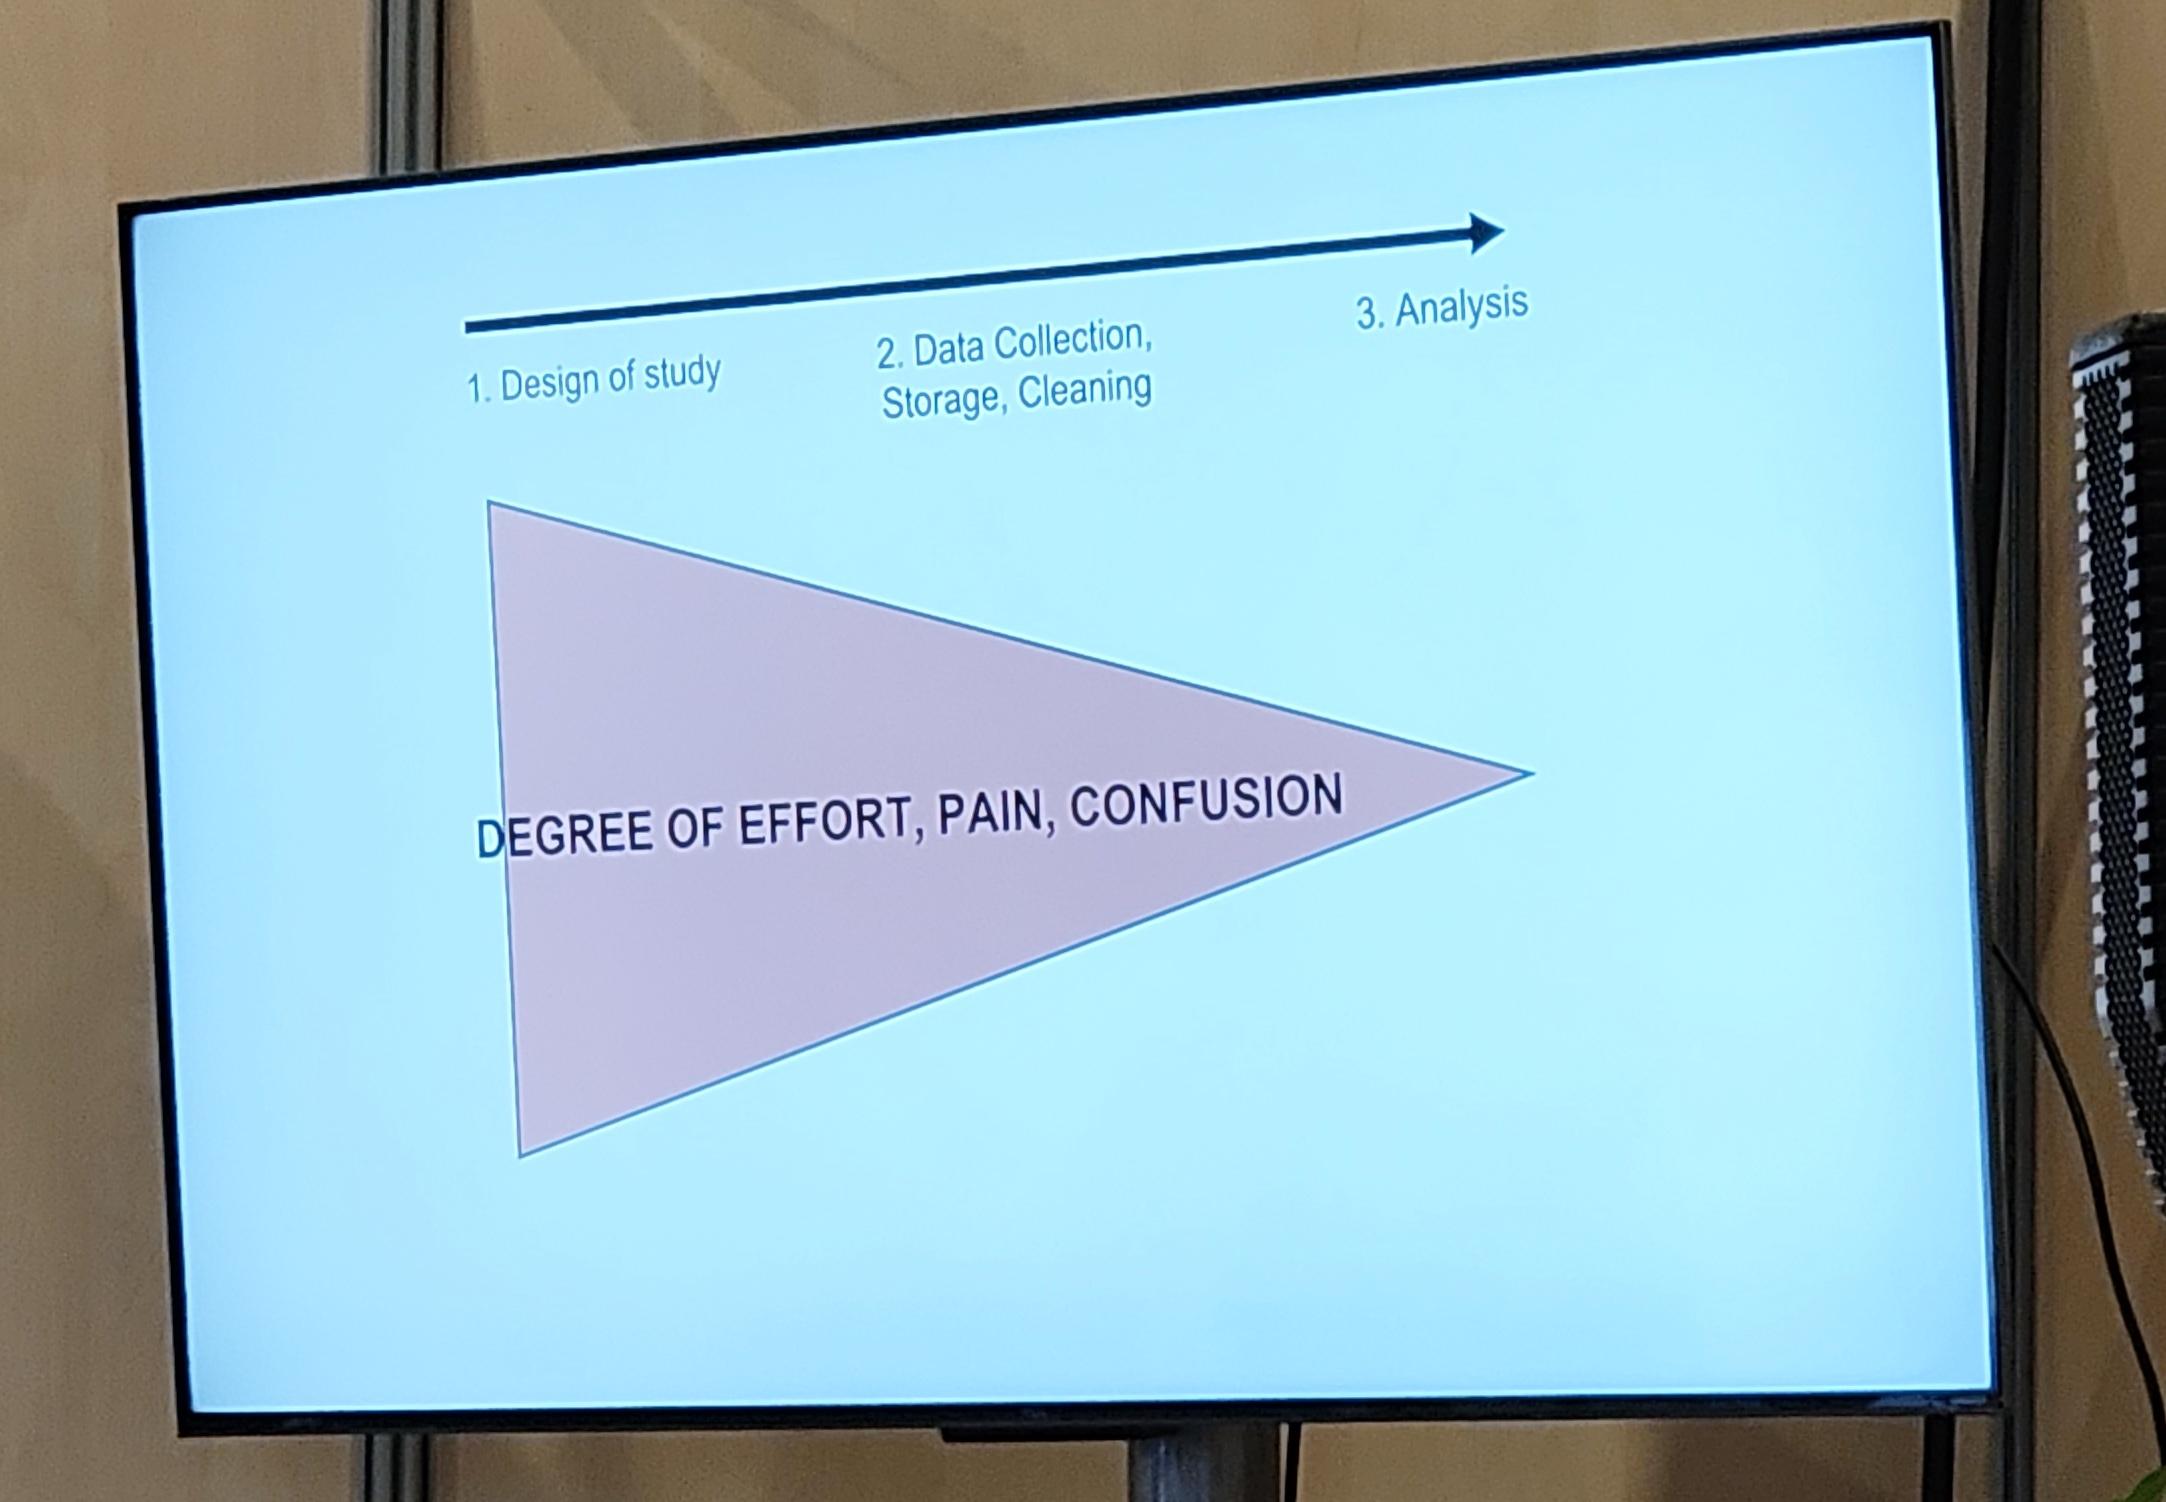
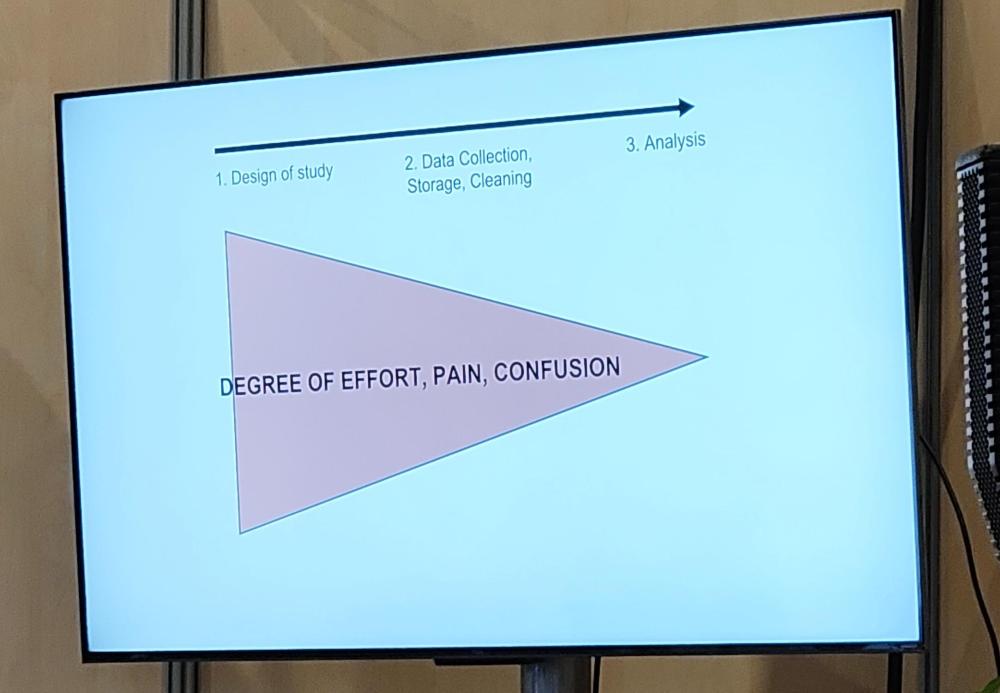
EBNEO had a thought-provoking session at the CEPAS conference, "Trustworthiness and Spin in Academic Publishing" Prof Gautham Suresh, president of EBNEO, dissected the importance of critical appraisal in clinical research and evidence-based practice. One key message was that good research starts with good study design, not with data analysis. Pre-specifying hypotheses and statistical analysis plans helps prevent p-hacking, selective reporting and the temptation to make the results fit the hypothesis. As the speaker emphasised, you cannot fix a poor study design with sophisticated statistical analysis. The session also highlighted the need to look beyond abstracts and p-values. Be alert to spin, predatory journals and the difference between absence of evidence and evidence of absence. Increasing concerns about research fraud and AI-generated publications make critical appraisal even more important. The take-home message for clinicians: don’t accept published findings at face value. Assess the validity of the study, the clinical importance of its results, and whether the evidence really supports a change in practice. We need less research, better research, and research done for the right reasons. Find some photos below!





-
This poster from the Medical University of Graz, Austria, explored whether early lung ultrasound (LUS) could help identify newborns at risk of ongoing respiratory distress. The study included 50 infants born at ≥34 weeks and with respiratory distress at birth. They all underwent lung ultrasound at 15, 30 and 60 minutes. Of these, 20 infants (40%) required continued respiratory support and NICU admission at 60 minutes. Lung ultrasound at just 15 minutes showed promising predictive ability, with an AUC of 0.81. Interestingly, none of the infants with a LUS score ≤5 required NICU admission, giving this cut-off a negative predictive value of 100% in this small cohort. However, a score ≥7 had only 56% sensitivity for predicting NICU admission. Taken together, these findings suggest that early lung ultrasound could become a useful bedside tool for identifying newborns who are likely to recover quickly, potentially avoiding unnecessary NICU admissions and separation from their parents. What do you think about these findings? Would the change your ways to evaulate infants or not?

-
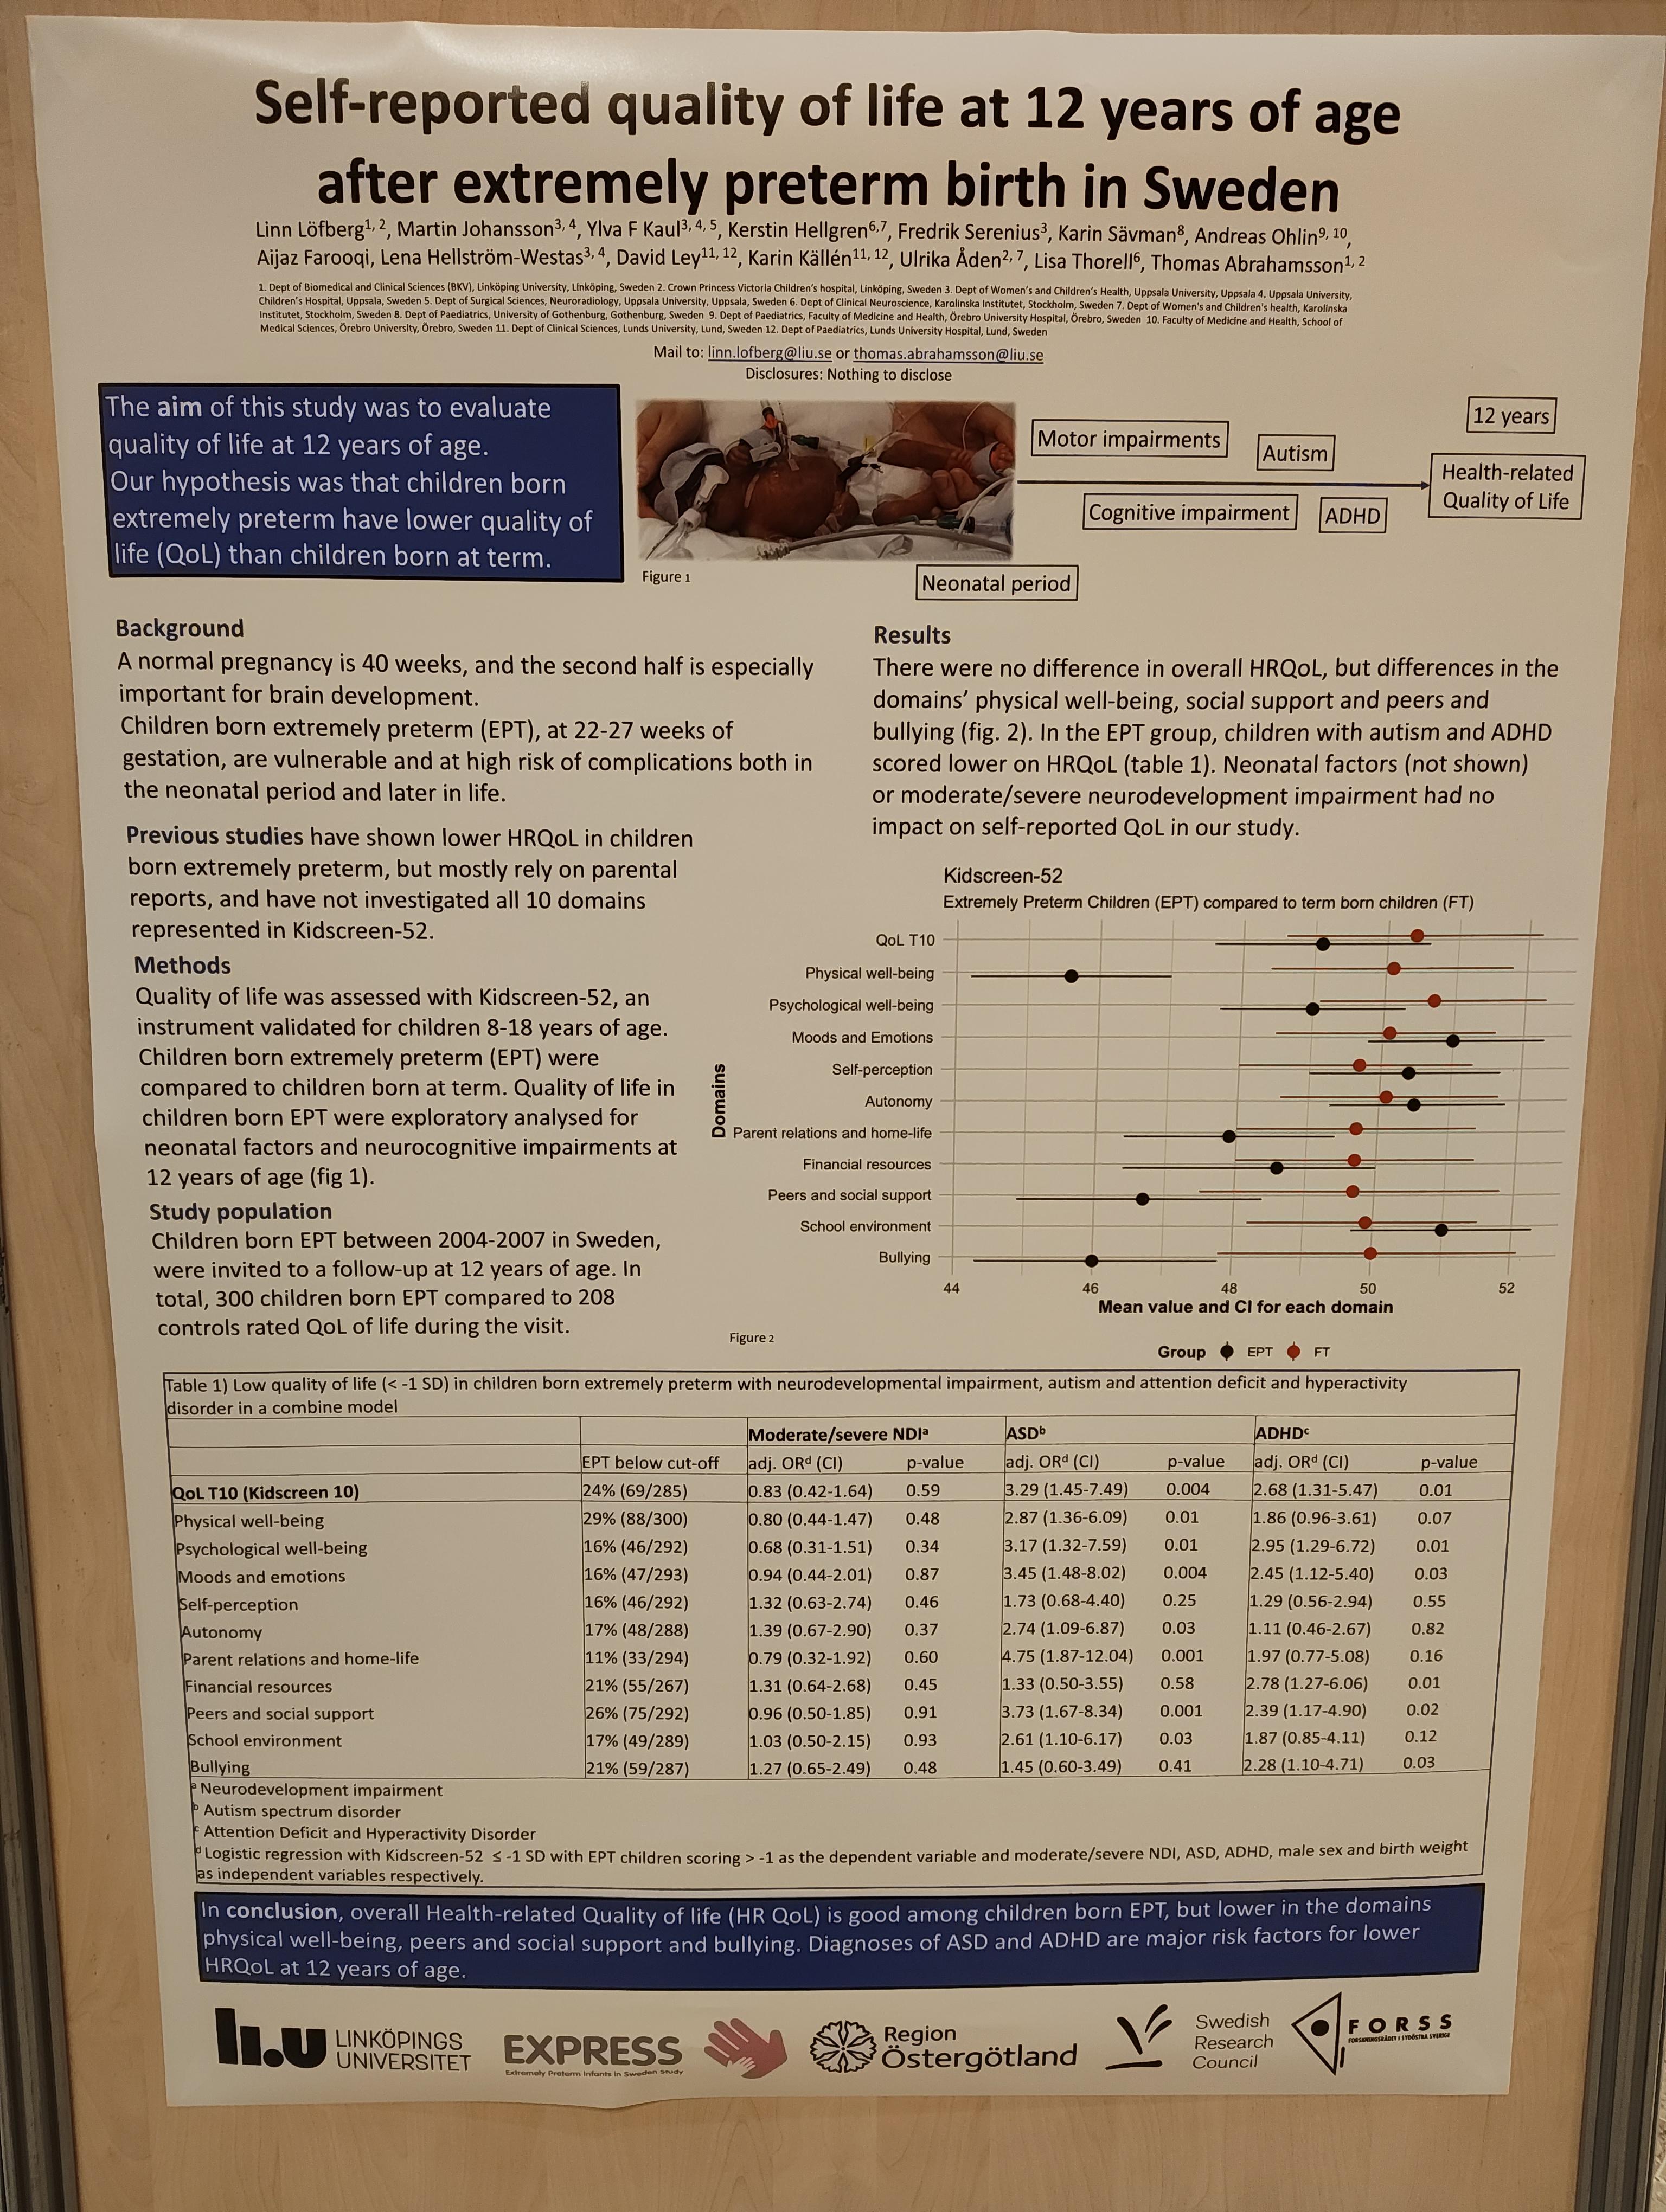
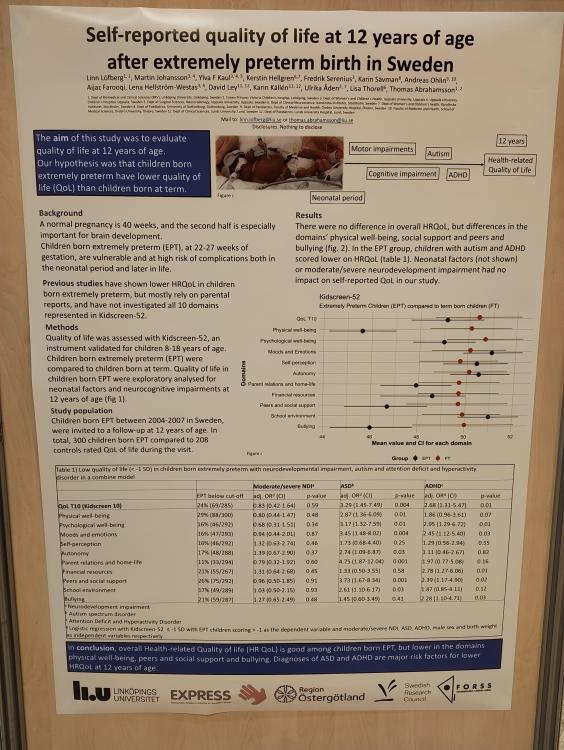
An interesting CEPAS poster from the Swedish EXPRESS cohort explored self-reported quality of life among 300 children born at 22–27 weeks of gestation, compared with 208 term-born controls. Using the Kidscreen-52 questionnaire, the researchers found that overall health-related quality of life was similar between the groups. However, children born extremely preterm reported lower scores for physical well-being, peer relationships/social support, and bullying. Also, children diagnosed with autism or ADHD were more likely to report difficulties across several domains. What do you think about these findings? I interpret results are encouraging! Despite a challenging start in life, most children born extremely preterm seem to perceive their quality of life similarly to their term-born peers. The findings also highlight the importance of listening to the children’s own perspectives rather than relying solely on parental reports. But I have one reservatiom, as always. The responses in surveys depends on who is actually responding. And this is not much disclosed in the poster (but I am sure, in the full paper to come)
-
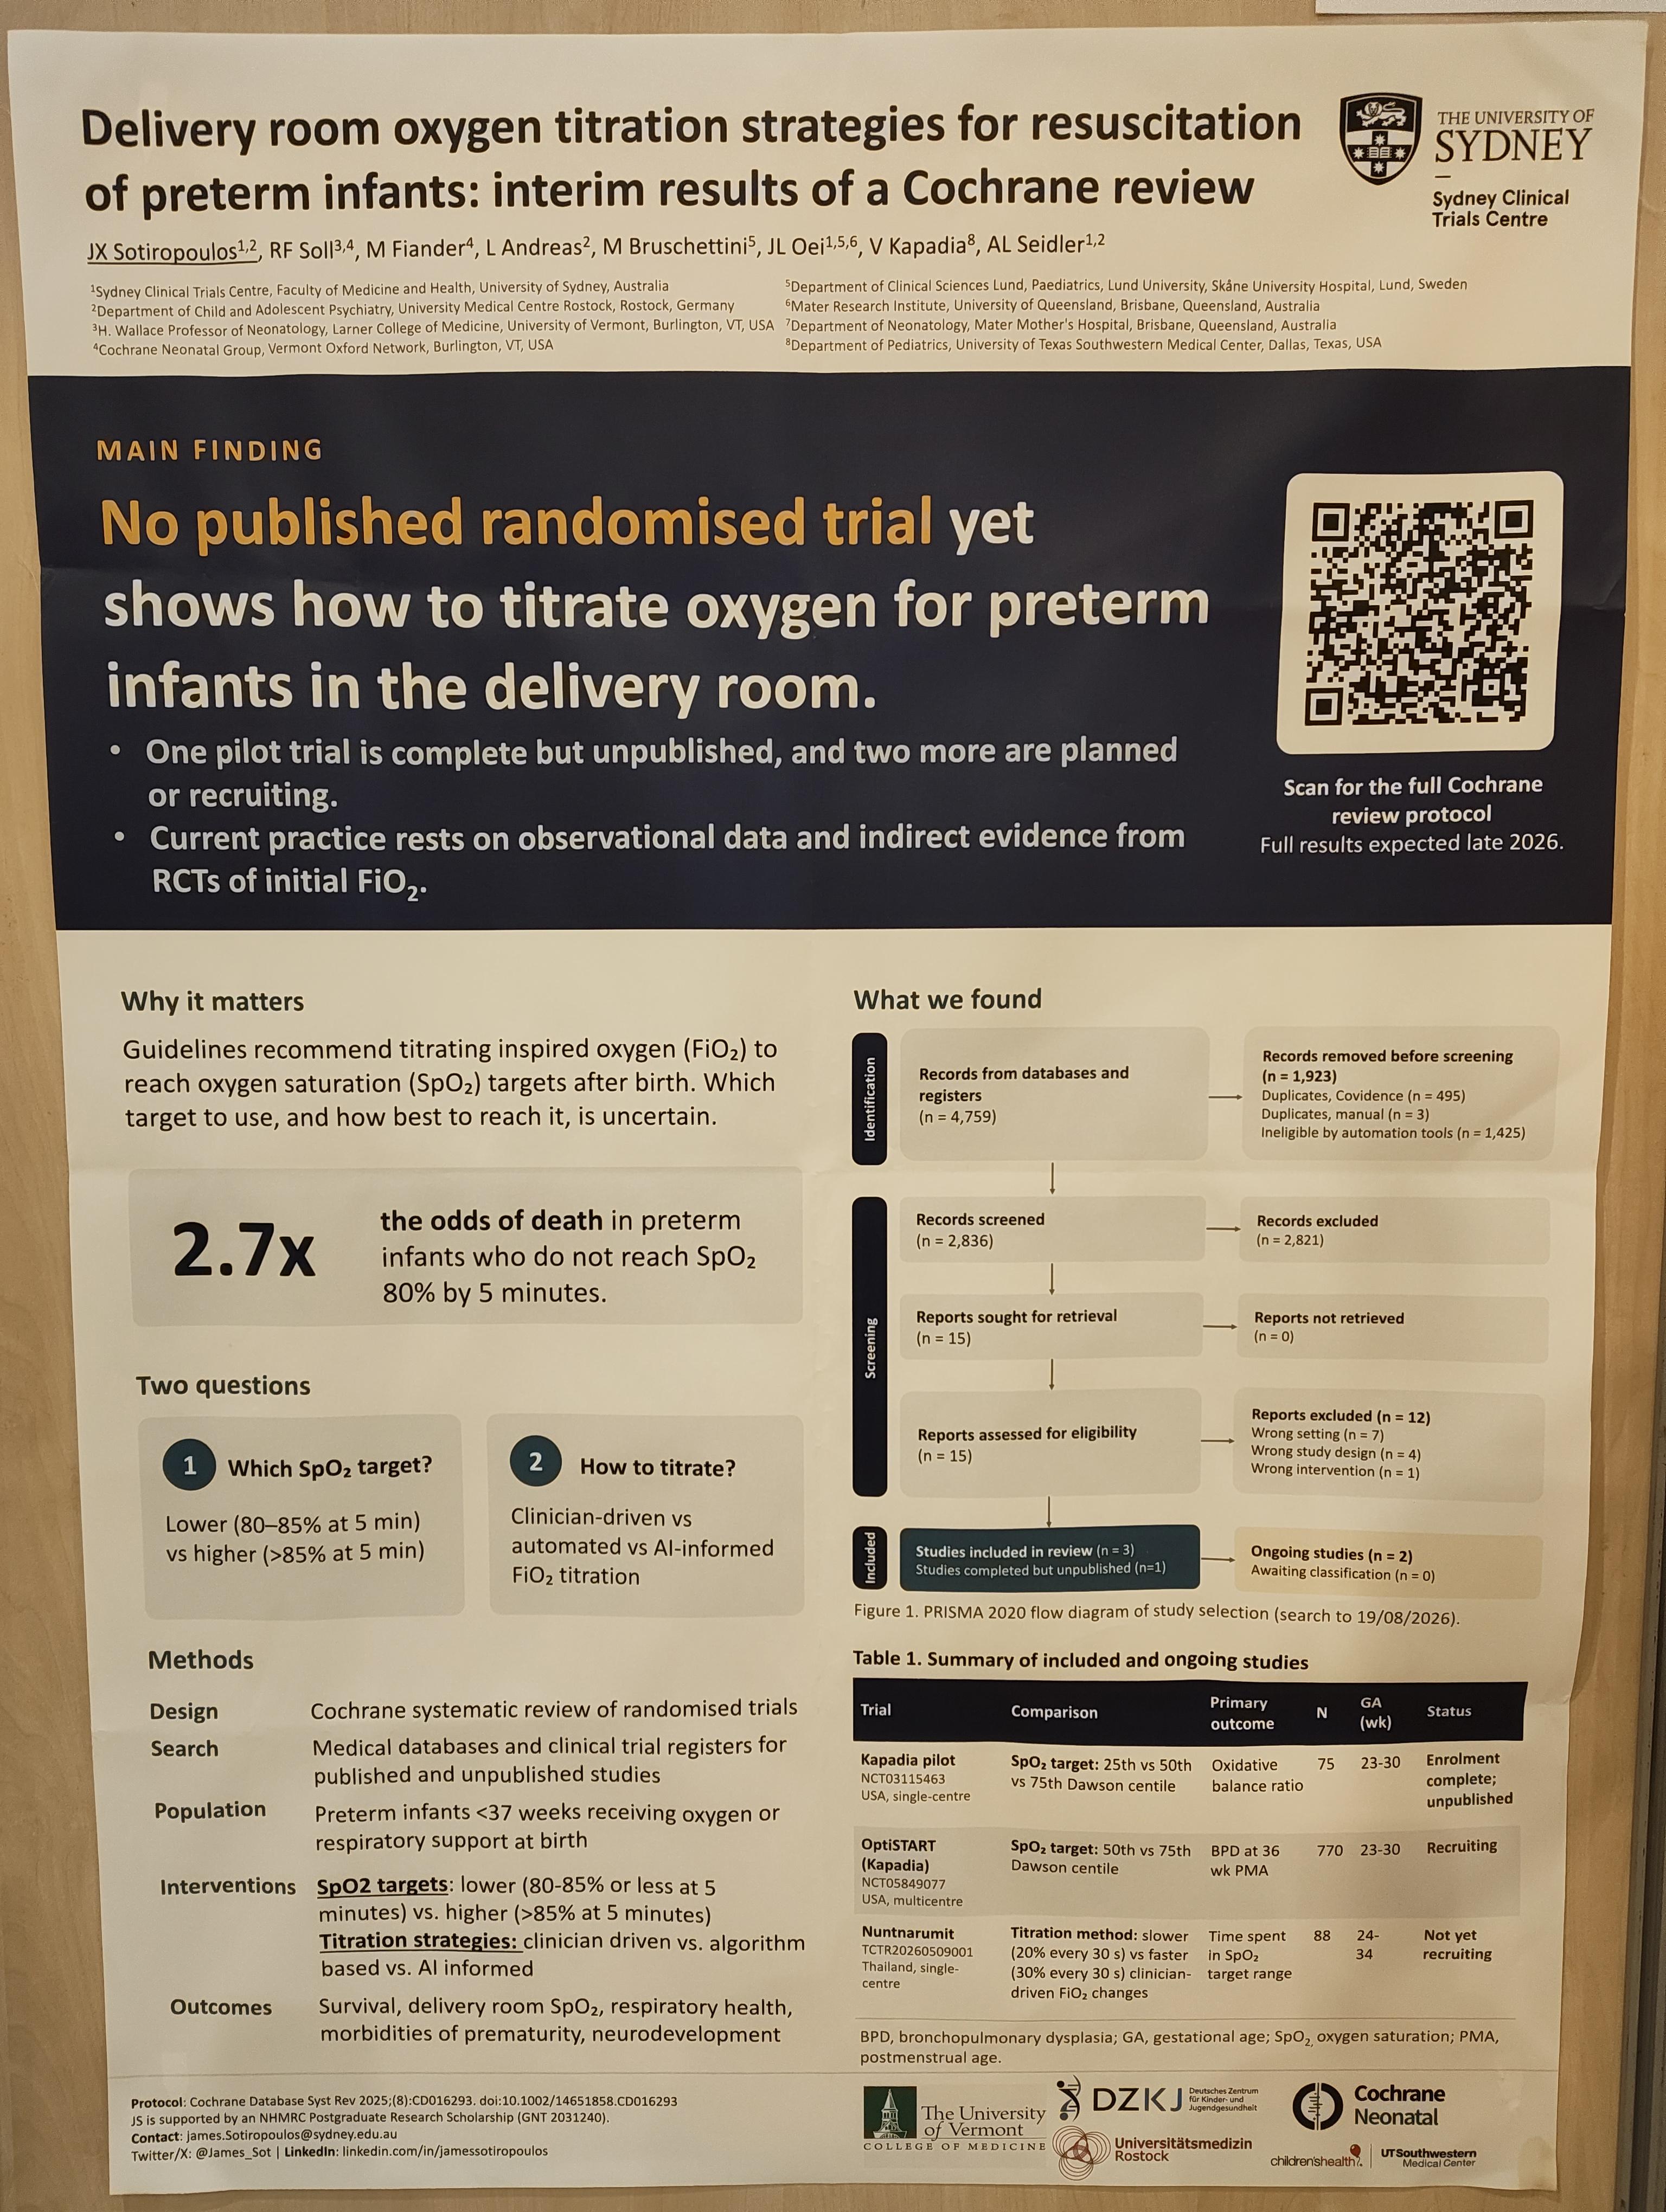
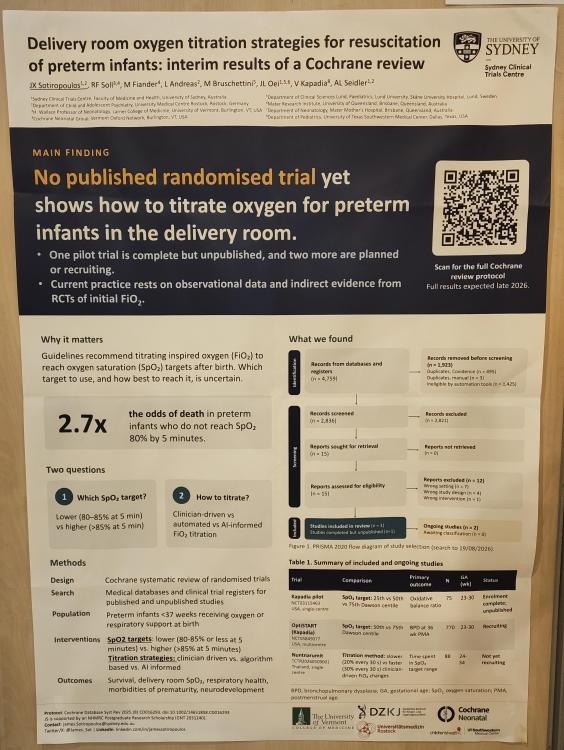
While CEPAS is yet to get going, some posters were already put up today. This interesting poster by Sotiropoulos and colleagues is an interim analysis of a coming Cochrane review. It highlights a significant evidence gap in neonatal resuscitation. Although guidelines recommend titrating oxygen (FiO₂) to reach specific SpO₂ targets after birth, no published randomised trials have actually investigated how best to do this. The ongoing Cochrane review looks optimal SpO₂ targets and different titration strategies, e.g. clinician-driven, automated and AI-informed approaches. So far, only one small pilot trial has been completed (but not published), while two further trials are planned or ongoing. So, much of what we do when adjusting oxygen in the delivery room is still based on observational data and indirect evidence rather than clinical trials. Link to the paper: https://www.cochranelibrary.com/cdsr/doi/10.1002/14651858.CD016293/full
-
There are a lot of great NICU and neonatology sessions and workshops at CEPAS 2026 (28–31 October). Here's a list of highlights! Wednesday, 28 October — Pre-congress workshopsTime Session / Workshop Main focus Priority 08:30–12:30 Non-Invasive Mechanical Ventilation — Part 1 Practical approaches to non-invasive respiratory support ⭐⭐⭐ 09:00–17:00 Neonatal Cranial Ultrasound Hands-on neuroimaging and interpretation in newborns ⭐⭐⭐ Thursday, 29 OctoberTime Session / Workshop Main focus Priority 09:00–12:00 Neonatal Procedural Skills Practical procedures and technical skills in neonatal care ⭐⭐⭐ 10:30–12:00 Hypoxic-Ischemic Encephalopathy: Evolving Therapies Emerging neuroprotective treatments beyond therapeutic hypothermia ⭐⭐⭐ 10:30–12:00 Congenital Diaphragmatic Hernia: Haemodynamics Cardiovascular management and pulmonary hypertension ⭐⭐ 10:30–12:30 Home Phototherapy Management of neonatal jaundice outside hospital ⭐ 14:30–16:00 Circulatory Failure in Neonates Haemodynamic assessment and treatment ⭐⭐⭐ Afternoon Stem Cell Therapies in Neonatology Emerging regenerative therapies ⭐⭐ Afternoon RSV Prevention New strategies for protecting infants against RSV ⭐⭐ Afternoon Care of the Tiny Baby — Workshop Practical management of extremely preterm infants ⭐⭐⭐ 16:30–17:30 Precision Drug Therapy in Neonates Individualized pharmacological treatment ⭐⭐ 16:30–17:30 Protecting the Tiny Brain Prevention and management of neonatal brain injury ⭐⭐⭐ Friday, 30 OctoberTime Session / Workshop Main focus Priority 09:15–10:45 Less Invasive Surfactant Administration Evidence and practical aspects of LISA ⭐⭐⭐ 09:15–10:45 Nutrition of High-Risk Neonates Nutritional strategies for vulnerable newborns ⭐⭐⭐ 09:15–16:45 Neonatal Neurocritical Care — Workshop Neuromonitoring, neuroprotection, and clinical management ⭐⭐⭐ Morning Neonatal Sepsis — Research Presentations New evidence on diagnosis, prevention, and treatment ⭐⭐⭐ Morning Neonatal Resuscitation — Research Presentations Recent developments in delivery-room management ⭐⭐ 14:00–17:00 Neonatal Skills Workshop Practical NICU procedures and clinical techniques ⭐⭐⭐ 15:45–16:45 Cardiovascular Research in Neonatology Emerging evidence in neonatal cardiovascular care ⭐⭐ 15:45–16:45 Family-Integrated Care Parental involvement and family-centered NICU practices ⭐⭐ 15:45–16:45 Reducing Iatrogenic Blood Loss Strategies to minimize blood sampling and transfusion requirements ⭐⭐⭐ 15:45–16:45 Non-Invasive Monitoring New approaches to monitoring critically ill newborns ⭐⭐ Saturday, 31 OctoberTime Session / Workshop Main focus Priority 10:30–11:30 Omics Approaches to Neonatal Sepsis Molecular approaches to improving sepsis diagnosis and management ⭐⭐ 10:30–11:30 Artificial Intelligence and the Neonatal Brain AI applications in neonatal neuroimaging and neurological assessment ⭐⭐⭐ 10:30–11:30 Cell Therapies in Neonatology Potential applications of regenerative medicine ⭐⭐ 11:45–12:30 Poster Walks Selected neonatal research presentations and discussions ⭐⭐ 12:45–13:15 20 Years of 99nicu Online professional communities and knowledge sharing in neonatology ⭐⭐⭐ 13:15–14:00 Cerebral Palsy: Early Detection and Intervention Advances in early diagnosis and treatment ⭐⭐⭐ 14:00–15:30 Long-Term Outcomes After Preterm Birth Neurodevelopmental and other outcomes following prematurity ⭐⭐⭐ 14:00–15:30 Necrotizing Enterocolitis NEC prevention, epidemiology, and emerging evidence ⭐⭐⭐ 14:00–15:30 Neonatal Transfusion Evidence and current approaches to transfusion practices ⭐⭐⭐ Note: Several sessions run in parallel, so the lists are a curated overview rather than a conflict-free personal schedule.
-
-
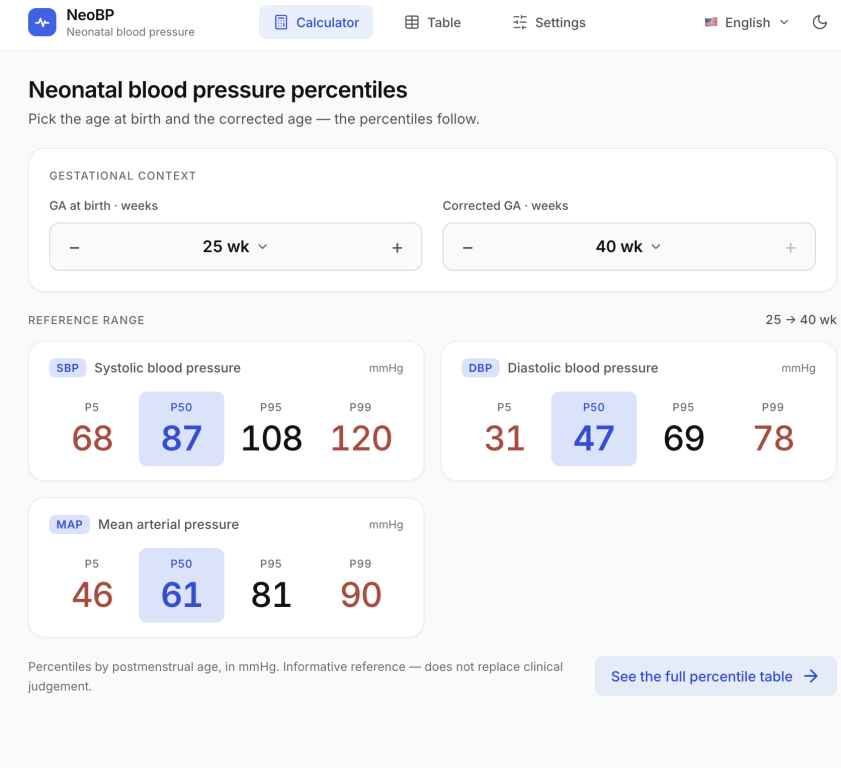 NeoBP is a free online tool that allows clinicians to consult neonatal blood pressure percentiles based on gestational age at birth and corrected gestational age. The charts are based on a study published by Hillman and colleagues in Neonatology in 2025: Oscillatory Blood Pressure Values in Newborn Infants: Observational Data Over Gestational Ages. This large observational study analyzed more than 1.4 million blood pressure measurements from 29,323 newborn infants, covering gestational ages at birth from 22 to 40 weeks, reporting percentiles for systolic, diastolic, and mean arterial blood pressure. One particularly relevant finding was that blood pressure rises rapidly during the first two weeks of life and depends not only on corrected gestational age but also on gestational age at birth. Transparency and disclosure: NeoBP is an independent, non-commercial project developed for educational and clinical reference purposes. I have no conflicts of interest to declare and no financial relationships with the authors or publisher of the original study.
-
Thanks for sharing this post, I like that you make the connection with India and Gandhi, I often regard preterm infants as unpriviliged, also in our high-resourced society in the so-called Rich World. Important that you stress the importance of sodium supplementation. I have observed a trend towards less supplementation, and that a driving factor is a "normal S-Na". I think there is a mission, for this low-cost and easily tolerated intervention.
-
Very interesting and often overlooked topic IMHO. We have a rather pragmatic approach to breast feeding practise in preterm infants, practically part of the skin-skin work. It is the nursing team who lead / assess the breast feeding practise and progress. If a mother wants to breast feed, we continue with tube feeding as a complementary feeding while breast feeding practise is ongoing, and typically reduce tube feeding volumes by 5-10 ml intervals depending on "what works" (based on unstructured infant assessment before meals, and daily weights). Importantly, we don't introduce bottle complementary feeding unless this is the request from parents, otherwise we "fade/phase out" the tube feeding successively. In complicated (rare) cases, we also refer a oral motor specialist (speech therapist).
-
Join me for a walk along my academic memory lane! In a series of posts, I want revisit my papers. My intention is to share a summary of main findings and their impact, if any 🙂 As my academic training was in epidemiology and biostatistics, my niche grew into methodological competence rather being disease orientated. So, you will notice that I have been working with a variety of topics. The very first paper was a result of unexpected clinical observations. In 2002, together with colleagues in Stockholm, I published a case series in Acta Paediatrica. We described suffering from water intoxication caused by excessive maternal drinking during labour. The case series included four term infants presenting with seizures and other neurological symtoms shortly after birth. Blood tests revealed severe hyponatraemia, from 105 to 121 mmol/L, clearly below the normal range. These infants had in common that their mothers had consumed unusually large volumes of water/fluids during labour. In two cases, the reported intake reached eight litres! One mother herself developed seizures from severe hyponatremia. Fortunately, all four infants recovered and had normal neurological development at follow-up during their first year of life. How could maternal water drinking affect the newborn? During labour, physiological hormonal changes make women potentially more vulnerable to water retention. Mechanisms involving vasopressin and oxytocin may reduce the ability to excrete excess water, that in turn can result in reduced maternal sodium levels from water retention. Since water and electrolytes are exchanged freely across the placenta, the infant can also develop hyponatraemia before birth. Around this time, young women carrying water bottles as an accessoir were frequently seen “downtown”, like a fashion trend signalling a healthy life style. Furthermore, women in labour were encouraged to drink fluids during labour, with a good intention: to prevent dehydration during a physically demanding process. Our case series illustrated that a well-intended advice could become harmful when taken to extremes. The publication even made some headlines in regular news in Sweden, spreading awareness to the public. Importantly, our message was not that women should avoid drinking during labour, but rather that fluid intake should be reasonable. Looking back, almost 25 years later, I still rank this small case series highly. The paper was not only my “first-born”, it also gained enough publicity to improve practises. Most importantly, this first step made me enter more complex research projects in a PhD project. The next post will be about the first project in my PhD. As the saying goes, stay tuned 🙂 Reference Johansson S, Lindow S, Kapadia H, Norman M. Perinatal water intoxication due to excessive oral intake during labour. Acta Paediatr. 2002;91:811–814. DOI: 10.1111/j.1651-2227.2002.tb03332.x
-
Where do you go when you want to discuss a new scientific paper, ask a clinical question, or exchange ideas with neonatal colleagues around the world? For 20 years, we have connected neonatal professionals across borders here in the 99nicu forums. Now, with NICUverse.org, we also have a space for instant communication – a place for spontaneous conversations about neonatal care, research, and everything else related to our professional lives. Imagine reading an interesting paper, perhaps one that challenges current clinical practice. You have questions, disagree with the conclusions, or simply want to share it with others. Why not share it on NICUverse and start a conversation? Share a paper. Ask a question. Challenge an interpretation. NICUverse complements the more structured discussions on 99nicu by making professional conversations easier, faster, and more spontaneous. Think of it as a virtual coffee room for the global neonatal community, open around the clock! But there is also a bigger idea behind NICUverse. Why should our professional conversations depend on commercial Big Tech platforms? The typical social media platforms have their own priorities, driven by advertising, algorithms, and commercial interests. NICUverse and 99nicu are different - independent and community-driven spaces, built for neonatal professionals rather than advertisers. After 20 years of 99nicu, I believe it is time to reclaim our online community. Not by abandoning other platforms, but by building something of our own. And a community is only as good as the conversations happening within it. 👉 Join the conversation at NICUverse.org
-
Here's the follow up program from Stockholm, it is in Swedish but the AI-bots will help you translate well. I think our program is slightlly more extended than outside Stockholm, but the 2y and 5.5y evaluations are standardised and goes into our national quality register. So, inclusion is based on risk group, like a routine We typically have a team appointment, with PT and doctor, and make the medical and motor assessment together. It is quite common that the PT gives advice on how to stimulate development and they often book up their own follow ups, inbetween team visits. uppfoljningsprogram-barn-utskrivna-fran-neonatalvardsavd.pdf

View in the app
A better way to browse. Learn more.